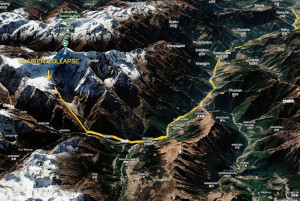
The immediate priority after the Bhotekoshi flood on August 26 was understandably rescue and emergency medical care. Yet the latest reporting from Rasuwa and Nuwakot shows that the public-health consequences are continuing: damaged roads and bridges have made hospitals difficult to reach, pregnant women have faced interruptions in antenatal and delivery care, displaced families remain in temporary shelters, and essential medicines and routine services have been strained.
That reality goes beyond Bhotekoshi, to the heart of how Nepal should understand climate change and disaster risk.
My experience in public health and infectious diseases has taught me an important lesson: many health risks do not appear suddenly. Small changes in the environment can alter disease patterns, shift the habitats of disease vectors and pathogens, and allow diseases once concentrated in particular geographical areas to emerge in new places.
The Bhotekoshi disaster makes this lesson particularly urgent.
It would be scientifically inappropriate to conclude that this flood was directly caused by climate change, without detailed attribution studies. Current assessments indicate that an ice-and-rock avalanche entered the Lhende catchment, temporarily blocked the river and generated a sudden surge of water, sediment and debris downstream. The International Centre for Integrated Mountain Development (ICIMOD) has stressed that the precise triggering processes and the contribution, if any, of longer-term warming require careful scientific assessment.
But one event does not have to be labelled a direct consequence of climate change for it to raise urgent questions about climate risk.
Floods do more than destroy homes and infrastructure. They contaminate drinking-water sources, damage sanitation systems, displace communities and interrupt health services.
The Bhotekoshi disaster has demonstrated how quickly these vulnerabilities can converge. Recent reports describe disrupted access to Trishuli Hospital and other referral services after roads and bridges were washed away. Some patients now face journeys that take hours longer than before the disaster. Such delays are particularly dangerous for obstetric emergencies, serious childhood illness, trauma and other time-sensitive conditions.
Under such conditions, the risk of diarrhoeal and other water-borne diseases can increase. Overcrowding, unsafe water, damaged sanitation and interrupted health services may also increase risks of respiratory and other communicable diseases, while stagnant water can create additional vector-breeding opportunities. These risks are especially important when displaced people remain in temporary shelters for prolonged periods.
But the post-disaster health crisis is not limited to infectious diseases.
People living with diabetes, cardiovascular disease and other chronic conditions may lose access to essential medicines and regular care. Pregnant women, children, older people and people with disabilities may face even greater risks when health systems are disrupted. Mental-health and psychosocial needs can persist long after rescue operations end.
The government’s decision this week to waive health-insurance co-payments and identification requirements for affected people in Rasuwa, Nuwakot and Dhading for three months is therefore an important recognition that financial and administrative barriers to care must also be removed during recovery.
The Bhotekoshi experience should change how Nepal measures disaster damage. Assessments should measure not only damage to houses, roads, bridges and hydropower facilities, but also disruption to the health system and continuity of essential services.
Could people reach hospitals when roads were cut off? Were medicines available when supply chains were disrupted? Could pregnant women, children and older people access essential care? Were drinking-water sources protected? Could health authorities detect outbreaks quickly? Were temporary shelters equipped with adequate water, sanitation and hygiene facilities?
These questions determine whether a natural hazard becomes a prolonged public-health emergency.
Another important health consequence of climate change is the changing geography and seasonality of disease.
Changes in temperature, rainfall and humidity can affect the survival, distribution and breeding conditions of mosquitoes and other disease vectors, as well as the pathogens they transmit. Climate is therefore one important influence on where and when transmission becomes more favourable, alongside urbanisation, population movement, land use, housing, water storage and the effectiveness of vector control.
Nepal’s experience with dengue offers an important warning. Peer-reviewed studies describe a substantial expansion of dengue beyond the traditional lowland belt, including hill and higher-altitude settings, with temperature, rainfall and ecological change interacting with urbanisation, mobility and water-management practices. The record 2022 epidemic demonstrated how rapidly a climate-sensitive disease can become a nationwide health challenge. Disease surveillance, therefore, should not begin only after patients arrive at hospitals.
The Himalayan health crisis must also be viewed in relation to environmental pollution. Research reported by ICIMOD at Nepal’s Yala Glacier estimated that black carbon contributed about 28 percent of total pre-monsoon melting under the conditions studied. This estimate is site- and season-specific and should not be generalised to every glacier or every year, but it illustrates the potential importance of short-lived climate pollutants in Himalayan cryospheric change.
Nepal should make climate change and disaster resilience a core issue of health policy. Information about weather and environmental changes should be connected with disease surveillance and routine health information. Systems should identify potential health risks early by combining temperature, rainfall, river, flood and other environmental signals with timely disease data, while avoiding over-reliance on any single indicator.
The current disaster shows why this matters. Response priorities include trauma care, continuity of essential services, disease surveillance, safe water and sanitation, maternal and child health, management of chronic disease, and mental health and psychosocial support. This requires stronger information-sharing among the health sector, the Department of Hydrology and Meteorology, disaster-management authorities, local governments, research institutions and communities.
Nepal rebuilds after every major disaster. But rebuilding exactly what existed before is no longer enough. The Bhotekoshi disaster should become a test of whether reconstruction is being planned for the risks of the future.
New roads, bridges, hydropower projects and settlements must be designed with future climate and multi-hazard risks in mind. Hospitals, health centres and medicine-supply systems must also be protected against floods, landslides, heat and other climate-sensitive hazards, including failures of access, power, water and communications.
Nepal has been seeking international climate finance and support, and such assistance is necessary. But climate assistance should not be limited to relief and reconstruction after disasters. A larger share should support prevention, preparedness, resilient health systems and locally usable early-warning capacity before the next emergency occurs.
The central question for Nepal’s climate strategy should be: How to protect the health of Nepalis from its consequences.
The answer does not lie in rescue alone. It lies in preparedness, scientific surveillance, resilient primary and referral care, cross-border cooperation and the creation of a climate-resilient health system.




 20.12°C Kathmandu